Eight quality improvement initiatives from real hospital and health-system strategic plans, with the frameworks used and what each team measured.
- Ownership is the clearest QI risk in our data. In 50 healthcare organizations on ClearPoint, 89.1% of strategic objectives have no named owner, the highest share among the sectors with 30 or more organizations in our data.
- Unowned initiatives almost never finish. Healthcare initiatives with a named owner were completed 11.7% of the time, against 0.9% without one.
- Quality-named projects follow the same pattern. Of 198 healthcare initiatives with quality, safety, infection, readmission or improvement in the name, none of the 105 without an owner was recorded as complete.
- Copy the structure of the published programs. The strongest examples below name their measures and a review cadence; add one owner per measure on top.
- Cut the reporting load before you add projects. Southern Ohio Medical Center went from one person spending 40 hours a month populating data to 15–20 minutes.
Updated November 2026.
Quality improvement (QI) in healthcare is the systematic, data-driven work of changing how care is delivered to reduce harm, cut waste and improve patient outcomes. Hospitals run it as ongoing programs and as targeted projects, usually with PDSA, Lean or Six Sigma, and prove it with measures such as infection, readmission and discharge rates.
The eight initiatives below come from published hospital and health-plan quality plans, peer-reviewed studies and one ClearPoint customer story. Before them, one finding from our own data that changes how you should read any QI example: in the 50 healthcare organizations that run their strategic plans on ClearPoint, 89.1% of strategic objectives have no named owner. That is the highest share among the sectors with 30 or more organizations in our data, and it shows up directly in completion rates.
Get the library of 108 healthcare KPIs to track your QI initiatives
What is quality improvement in healthcare?
A healthcare QI program is a set of focused activities that monitor, analyze and improve care processes so outcomes improve. Teams gather data in a defined area, test a change, and keep the change only if the measure moves. QI comes in two forms:
- Organization-wide, ongoing programs: long-running work across the whole organization on patient safety, patient experience or efficiency, usually reviewed by a quality committee each month or quarter.
- Process-specific projects: time-boxed efforts on one problem, such as catheter use or discharge instructions, with a baseline, a target and an end date.
Both matter because regulators and payers increasingly pay for outcomes rather than procedures, and accreditors such as The Joint Commission, NCQA and CMS evaluate whether quality programs are in place and working.
How do you measure healthcare quality?
Most QI programs measure five things:
- Clinical outcomes: mortality, readmission and complication rates.
- Patient experience: survey scores on communication, discharge information and overall care.
- Safety: adverse events, medication errors and hospital-acquired infections.
- Efficiency: wait times, length of stay, emergency department boarding.
- Equity: gaps in access and outcomes across patient groups.
The measure list is rarely the hard part; our 30 healthcare KPIs with formulas cover the usual set. The hard part is keeping each measure current. Of the 23,542 healthcare measures in ClearPoint’s research database (demo and training scorecards excluded), 73.1% have no named owner. Without an owner, nobody is assigned to write the explanation when one of those measures turns red.
Why do so many quality improvement initiatives stall?
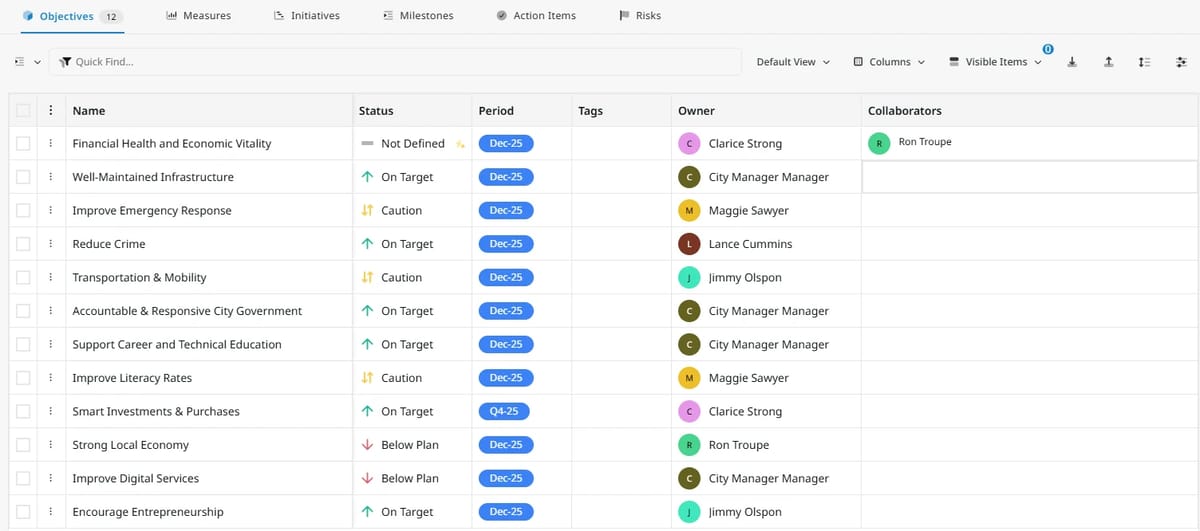
QI literature usually lists resistance to change, staff time, and data quality. Those are real. But when we look at how healthcare plans are structured in ClearPoint, one gap explains more than any of them: no single person is responsible for the initiative.
Healthcare initiatives: completion rate by ownership
Share of initiatives marked complete, healthcare organizations on ClearPoint
Source: ClearPoint Strategy research database, 2017–2024 (n = 6,163 healthcare initiatives in the 47 of 50 healthcare organizations that track initiatives; quality and safety subset n = 198 initiatives in 29 organizations whose names include quality, safety, infection, readmission, patient experience or improvement, demo and training scorecards excluded).
Across 6,163 healthcare initiatives, those with a named owner were completed 11.7% of the time; those without one, 0.9%. For the 198 initiatives explicitly about quality, safety, infection, readmission or improvement, none of the 105 unowned ones was recorded as complete, against 8.6% of the 93 owned ones. Completion flags undercount real work, since many teams never close items out, but the gap between owned and unowned is too wide to be a reporting quirk.
Healthcare also stands out against other sectors. Among the sectors with 30 or more organizations in our data, it has the highest share of strategic objectives with no named owner.
Strategic objectives with no named owner, by sector
Share of objectives with no owner assigned, organizations on ClearPoint
Source: ClearPoint Strategy research database, 2017–2024 (n = 52,247 objectives across ~318 organizations; sector counts in labels).
Healthcare plans leave ownership blank more often than city governments, universities or banks do. If your QI work sits under a strategic objective with no owner, nobody above the project team is accountable when it drifts.
Which quality improvement frameworks do hospitals use?
- Plan-Do-Study-Act (PDSA): plan a change, try it on a small scale, study the result, then adopt, adapt or drop it.
- Lean: remove steps that add no value for the patient, such as waits, handoffs and rework.
- Six Sigma: reduce variation and defects with statistical process control.
- The Baldrige Excellence Framework: an organization-wide model for performance excellence that includes quality.
Pick the framework that suits the problem. Then give each measure and each project a named person and a review date, because none of the four frameworks does that for you.
8 examples of quality improvement initiatives in healthcare and hospitals
Here are eight QI programs and projects, each with a public source. For each, note what was measured and who reviewed it.
Organization-wide, ongoing programs
1. Florida Department of Health
The Florida Department of Health built its 2022–2026 State Health Improvement Plan after a health assessment covering all 67 counties. The plan sets seven priority areas, each with up to four goals and three objectives:
- Alzheimer’s Disease and Related Dementias
- Mental Wellbeing and Substance Abuse Prevention
- Chronic Diseases and Conditions
- Transmissible and Emerging Diseases
- Injury, Safety and Violence
- Maternal and Child Health
- Social and Economic Conditions Impacting Health
Progress is reported to priority-area workgroups on objective status, activity progress and key accomplishments, which is the cadence piece most QI programs skip.
2. Joseph Brant Hospital (JBH)
Ontario hospitals publish a Quality Improvement Plan (QIP) every year. JBH’s 2024/25 QIP work plan set six indicators, from alternate level of care days to workplace violence. The quality dimension in the left column is our grouping; the indicator wording is the hospital’s.
| Quality Dimension | Indicator |
|---|---|
| Timely (access and flow) | Total number of alternate level of care (ALC) days contributed by ALC patients within the specific reporting month/quarter |
| Equitable | % of staff completing Anti-Racism Learning Module |
| Patient-Centred | Did you receive enough information from hospital staff about what to do if you were worried about your condition or treatment after you left the hospital? |
| Safe | Patient falls with harm level of moderate or worse per 1,000 inpatient days Medication reconciliation at discharge (Best Possible Medication Discharge Plan created, as a share of patients discharged) Number of workplace violence incidents reported by hospital workers within a 12-month period |
3. L.A. Care Health Plan
L.A. Care Health Plan serves vulnerable and low-income residents of Los Angeles County. Its 2022–2024 Quality Improvement Program (a cycle that has since concluded; details as documented at the time) monitored the equity, quality and safety of care across four strategic directions, each with goals and objectives, and the QI team collected and analyzed data continuously to plan interventions.
L.A. Care Health Plan
Strategic Direction 3: Provide services and care that meet the broad health and social needs of our members.
Goal 3.1: Operate all components of California Advancing and Innovating Medi-Cal (CalAIM) as they are launched.
Objectives:
- Maximize care for L.A. Care members, within funding constraints, through successful implementation of Enhanced Care Management (ECM) and Community Supports for specified populations of focus.
- Ensure CalAIM Population Health Management (PHM) requirements are met.
- Monitor and establish infrastructure for longer-term CalAIM initiatives.
4. Blue Care Network of Michigan
Blue Care Network of Michigan publishes a Commercial HMO Quality Improvement Program Description each year. The 2026 edition covers access, clinical quality, satisfaction, service, qualified providers and compliance. The Board of Directors delegates the program to a Health Care Quality and Service Improvement Committee, with subcommittees for clinical quality, utilization management, behavioral health, credentialing, pharmacy and member experience; the Clinical Quality Committee meets at least six times a year. The Board approves an annual evaluation of the program’s effectiveness, and each year’s plan is built on the previous year’s evaluation.
Get the ebook of balanced scorecard strategy maps for healthcare organizations
Process-specific projects
5. Beth Israel Deaconess Medical Center
A Commonwealth Fund case study describes how the Boston hospital organized quality work: multidisciplinary teams that trace problems to root causes, a physician-led Health Care Quality department, the six Institute of Medicine quality domains as its framework, centralized data analysis paired with unit-level action plans, and unit dashboards. The study also notes involvement in quality from both the CEO and the board.
6. Mount Sinai
Mount Sinai’s “Lose the Tube” project targeted catheter-associated urinary tract infections (CAUTI) on hospitalist-led units, where catheters were placed in patients who did not need them and left in too long. New nursing documentation and physician-order steps cut the CAUTI rate from 2.85 to 0.32 per 1,000 catheter days, and mean catheter days per patient fell from 3.3 to 2.9 (American Journal of Infection Control, 2017).
7. Southern Ohio Medical Center
Southern Ohio Medical Center (SOMC), a nonprofit health system, managed performance improvement across a complex organization with hundreds of measures, decentralized efforts and heavy use of spreadsheets, which made it hard to prove compliance in regulatory audits. It centralized more than 400 scorecards and their metrics in ClearPoint as its single source of truth. Its Manager of Performance Improvement described the reporting load before the change: “It took one person 40 hours a month to populate all that data in all the places it needed to go.” Automation such as the Data Loader cut that to 15–20 minutes.
8. DaVita dialysis clinics (Poland)
In 2018, DaVita’s dialysis clinics in Poland introduced a new transplant referral pathway to meet referral timelines, keep patients active on the waiting list and make sure patients could be reached for surgery when their clinic was closed. Over 30 months, 69 patients were called for a deceased-donor transplant outside clinic hours through the new process, about a quarter of those transplanted (Transplantation Proceedings, 2022).
How do you set up a QI program so the projects get finished?
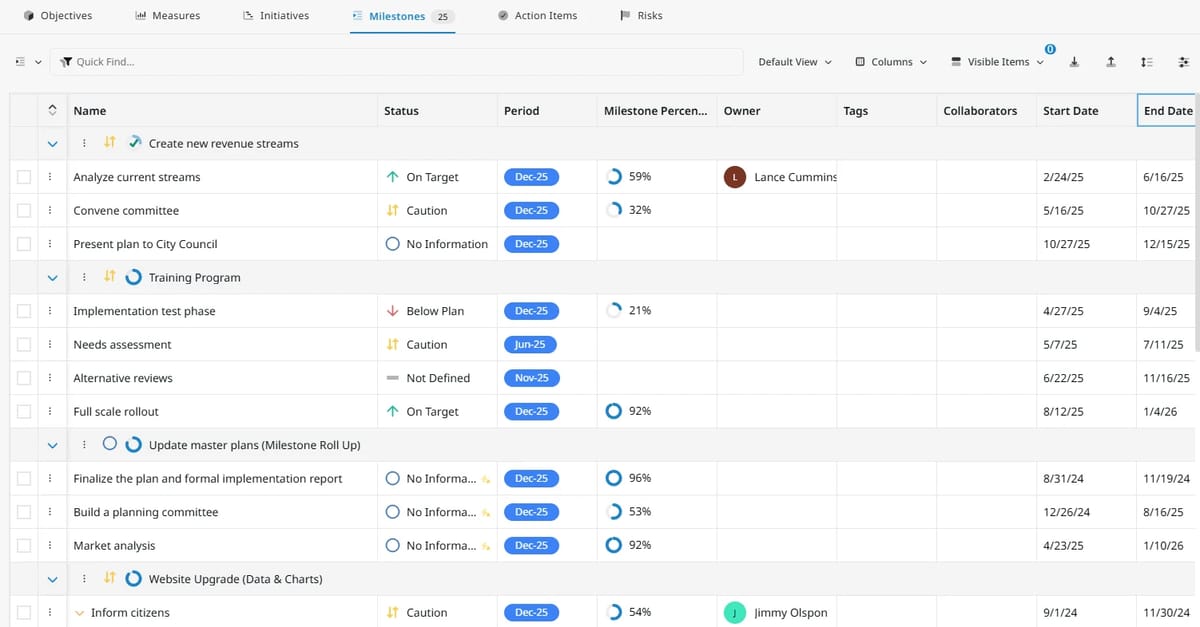
The five steps below follow the structure our customer success team walks through with hospitals in onboarding calls: each measure gets an analysis of where it stands and why, then an action plan, and when the fix needs several departments, an initiative linked to that measure with start and end dates and a responsible person. A performance improvement lead at a regional health system set up her cross-department stroke, STEMI and sepsis teams this way, as initiatives on one organization-level scorecard.
1. Link every QI project to one strategic objective
Write down which objective each project serves (patient safety, experience, access, cost). If a project serves none, question why it is funded. Our guide to building a healthcare strategic plan from the data shows how to keep that list short.
2. Name one person per objective, measure and project
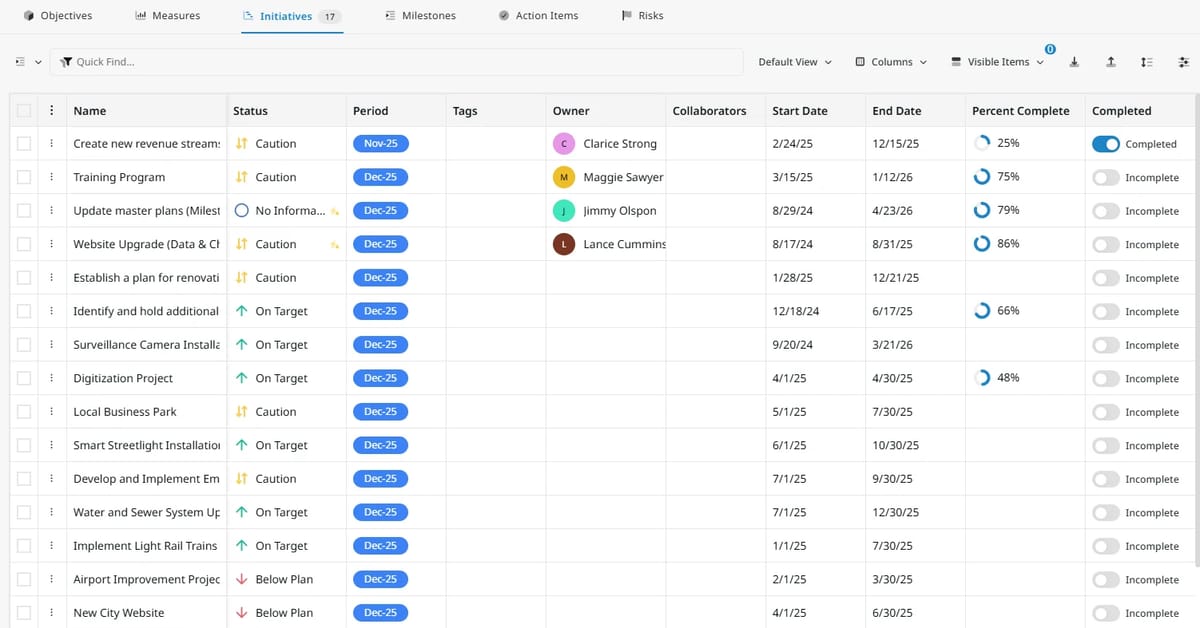
Name a person for each item; a committee or a service line cannot answer for an update. With 89.1% of healthcare objectives and 73.1% of healthcare measures unowned in our database, this step closes the biggest gap. The owner does not have to be the director whose scorecard the measure sits on: give it to the manager who actually enters the number. Committees still do the improvement work.
3. Put updates on a fixed cadence and automate the data collection
Monthly for clinical measures, quarterly for strategic objectives. Then remove the manual work that makes updates late. At Southern Ohio Medical Center (example 7), automating data collection cut the time one person spent populating data from 40 hours a month to 15–20 minutes. Carilion Clinic manages around 300 scorecards in ClearPoint.
4. Require a written explanation on every red measure
A red status with no sentence on cause and next step gives the quality committee nothing to act on. Ask each owner for both, and review only the red items in the quality meeting.
5. Publish results to staff, physicians and, where you can, patients
Share wins and misses alike. Our piece on healthcare dashboards that track outcomes instead of activity covers what to show at each level.
Where does ClearPoint fit in a healthcare QI program?
ClearPoint holds the plan: objectives, measures and QI projects linked to each other, each with an owner, updated on a schedule and rolled into scorecards and reports for the quality committee and the board. Owners get reminders and a list of what they need to update; the reports build from live data. It works alongside your EHR and clinical analytics as the place where the plan, its owners and its review cadence live. See how health systems use it on our healthcare page.
Get the library of 108 healthcare KPIs and give every QI measure a named owner
Frequently asked questions
What is quality improvement in healthcare?
Quality improvement (QI) in healthcare is the systematic, data-driven work of changing how care is delivered to reduce harm, cut waste and improve patient outcomes. It runs as organization-wide programs (patient safety, patient experience) and as time-boxed projects aimed at one problem, such as catheter-associated infections or discharge delays.
Why do healthcare quality improvement initiatives stall?
In ClearPoint's data, the clearest structural gap is ownership: 89.1% of strategic objectives in healthcare organizations on ClearPoint have no named owner, and healthcare initiatives without an owner were completed 0.9% of the time, against 11.7% with one.
What are examples of quality improvement initiatives in hospitals?
Published examples include Mount Sinai's "Lose the Tube" project, which cut catheter-associated urinary tract infections from 2.85 to 0.32 per 1,000 catheter days, Joseph Brant Hospital's six-indicator 2024/25 quality improvement plan, DaVita Poland's after-hours transplant referral pathway, and L.A. Care Health Plan's Quality Improvement Program.
Which frameworks are used for healthcare quality improvement?
The most common are Plan-Do-Study-Act (PDSA) cycles, Lean, Six Sigma and the Baldrige Excellence Framework. The framework matters less than giving each measure and project one named owner and a fixed review cadence.
How should a hospital track QI measures?
Link each QI project to the strategic objective it serves, give every measure one owner, collect updates on a schedule, and require a written explanation on any measure that turns red. Southern Ohio Medical Center cut the time spent populating its performance data from 40 hours a month to 15–20 minutes by moving that work into ClearPoint.
Where does ClearPoint's data come from?
The figures come from ClearPoint's anonymized research database of 20,582 strategic plans run on the platform between 2017 and 2024. We analyze the structure of plans (owners, statuses, completion flags), never their content. Healthcare cuts cover 50 organizations; sector counts are shown with each figure.
See how ClearPoint tracks your health system’s quality plan — book a demo
Common questions
How do we decide which quality improvement project to start with?
Start where a gap in safety, effectiveness, access or patient-centeredness meets a priority in your strategic plan. Review patient population and operations data for recurring problems, such as long wait times or frequent chronic conditions. Then choose the issue leadership can tie directly to the organization's vision, so staff see why it matters and resources follow.
Should an existing committee run our QI project, or should we create a new one?
Either works, as long as the group includes every role involved in the problem. Use an existing management structure when the issue sits inside one service line, and form a dedicated committee when it crosses departments. Whichever you choose, give the group a way to track its measures and report results against the goals it was set up to move.
Who should own each QI measure, a committee or a person?
A person. Assign every measure and initiative in the program to one named individual rather than a team or committee, so someone is answerable when results stall. Committee members can still contribute, but one name goes on each line. Review the assignments regularly and replace any owner who hasn't updated their data in 90 days.
Should we use PDSA, Lean or Six Sigma for a QI project?
Match the method to the problem. Use PDSA to test a change on a small scale and learn from it quickly. Use Lean when the problem is waste, delays or patient flow. Use Six Sigma when it is variation or defects in a repeatable process. The Baldrige framework suits organization-wide performance programs rather than single projects.
How do we show that a QI project actually worked?
Measure the problem before you change anything, then track the same measure on a fixed schedule afterward. Mount Sinai's catheter project changed nursing documentation and physician orders, and reduced CAUTI rates from 2.67/month to .2/month. Report the result to staff alongside the process change, so people can see which change drove the improvement and keep doing it.