Learn how to perform a gap analysis in healthcare. Identify where your organization stands and the steps needed to reach your strategic goals.
- Name one owner for each gap before assigning actions. Red healthcare measures with a named owner recovered to green 37% vs 18% without one.
- Set the next review date and reviewer before the meeting ends. Re-checked red measures recovered 24% of the time vs 1.9% when left alone.
- Find the root cause before funding a fix. Treating the symptom brings the same red number back next quarter under a new name.
- Cut the scorecard to measures you can own and re-check. Carilion Clinic cut its scorecard from 70 measures to 7, each tied to strategy.
- Benchmark targets with the free 108 Healthcare KPIs and Measures library. Every target needs a named standard, such as a regulatory threshold or national benchmark.
A healthcare measure goes red. Someone notices, and there's a meeting. Then, too often, nothing happens. A year later the number is still red, in the same report, in the same shade of red.
We wanted to know why. We pulled every measure that had ever gone red across 50 healthcare organizations on the ClearPoint platform, 6,096 of them. Then we looked at which ones clawed back to green and what was different about them.
The framework made no difference. Every organization ran some version of the same gap analysis. Two plain things separated the gaps that closed from the gaps that festered: whether the gap had an owner, and whether anyone kept checking it. Measures with a named owner recovered twice as often. Measures their teams kept re-checking recovered about thirteen times as often as the ones left alone after a look or two.
The gap analysis is the easy part, and almost everyone does it. Finishing it is where an owner makes the difference. The five-step method below is built around the two steps that decide the outcome.
Get the library of 108 healthcare KPIs to measure your gaps against
What is a gap analysis in healthcare?
A gap analysis in healthcare compares where performance is against where it should be. Then it names who will close the difference and when they'll check it again. It turns a vague "something's off" into a specific problem with an owner and a date.
On paper, it's three questions: what's happening, what should be happening, and what's holding the two apart. The question that predicts whether the gap ever closes is a fourth one, and most guides skip it: who owns closing it?
Here is an example. Say your objective is to cut 30-day readmissions by 15% this year. Halfway through, you've managed 4%. That 11-point shortfall is the gap. The analysis asks why (discharge instructions, follow-up scheduling, medication reconciliation, social factors) and turns the likeliest cause into a project with one name on it.
To write yours down, use our free gap analysis template. Its community hospital example includes a readmission row, filled in from the current state and the target to the gap type, the owner and the due date.
One distinction before you start. A gap in care is the distance between best-practice clinical care and what a patient actually receives, such as a missed screening. That's a clinical-quality problem with its own strategy. This guide is about gaps in process, service, and strategic performance: the operating layer that decides whether your plan moves at all. The measures in that layer tell a rough story.
56% of the healthcare measures teams actually track are off target right now. That's fine, because surfacing gaps is the point. What decides whether a red measure recovers is a named owner and a regular re-check. Finding a gap is not the hard part. Closing it is, and the data below shows what makes that happen. The five steps are built around it.
How to perform a gap analysis in healthcare, in 5 steps
The method is simple. The discipline is harder. If you run many facilities, programs, or service lines, do this per unit. A system-wide average hides the gaps that matter.
1. See the gap — and how long it's been there
Start with your measures and their red-amber-green statuses. Red or yellow flags the gap. Today's color matters less than the trend, and three months of red is a different problem from three years. A measure that just slipped needs a nudge. A measure that's been red since 2023 has a structural cause, and almost certainly no owner.
2. Define the target — and the standard behind it
Name the desired state, and name where the number comes from: a regulatory threshold, a national benchmark, an accreditation bar for PHAB or The Joint Commission, or a board ambition. "Better" is not a target. "At or below the NDNQI median of roughly 3.3 falls per 1,000 patient days" is.
3. Find the cause before you fund a fix
The red number is the symptom. Spend your energy on the cause. Ask why, then question the answer, then question that. Pull in the people who live in the process (nurses, schedulers, clinicians, administrators) and read the policies that quietly shape the work. Our data can't see this step from the outside, and it's where recurring gaps start. Skip it and treat the symptom, and the same red number is back next quarter under a new name. The data can see the next two steps, and the results are clear.
4. Put one name on it
Assign an owner before you assign actions. This isn't bureaucracy. It's the clearest split in the data. Among healthcare measures that had gone red, the ones with a named owner recovered to green 37% of the time; those without one, 18%. One decision doubles the odds. (Owned objectives show the same pattern: on track 67% of the time versus 44% without.) Then build the plan. Weigh each option's cost against what you have, and be willing to pull budget off lower-priority work if this gap is core to a strategic objective.
5. Set the next review date before you leave the room
This step matters most, and the data is blunt about it. Healthcare measures their teams kept re-checking recovered 24% of the time. The ones that got one or two looks and then silence recovered under 2%. Before the meeting ends, set the date you'll look again and name who will be looking. Pick a real date, not "quarterly, probably."
What makes a healthcare gap close
Most guides end on the same advice: "Run gap analyses regularly." It's true, but it doesn't help. The useful question is why the analyses you already run don't stick, and the platform data answers it. We took the 6,096 healthcare measures that had ever gone red and sorted them by what their teams did next.
Two plain findings decide it: an owner and a re-check. The gaps that never close aren't the hard clinical ones. They're the ones that left the room without a name and a next date. The framework is not on this chart. Everyone has one, so it isn't the variable.
"A few years ago I sat in a quarterly review with a county health department. One measure — immunization follow-up — had been red for three reviews running. Everyone in the room could explain why. So I asked the only question that matters: whose name is on it? Silence. It had belonged to 'the team' for a year, which means it belonged to no one. We put one coordinator on it and a standing monthly check-in — two quarters later it was green. The analysis had been right the whole time. It just never had an owner. That's the pattern: the gaps that stay red aren't the hard ones, they're the ones that left the room without a name and a date." — Joseph Lucco, VP of Customer Success, ClearPoint Strategy
So the advice is this: don't run a gap analysis until you've decided who will own the gap and when you'll check it again. Without those two commitments, you're documenting a gap, not closing it.
Real healthcare gap analyses
Here is what it looks like when health systems run it.
Carilion Clinic: from 70 measures to 7
Carilion Clinic is a not-for-profit health system in Roanoke, Virginia, with around 13,000 employees and a level-one trauma center. Its clinic scorecard had swollen to 70 measures. The gap wasn't a missing number. There were too many to act on, so none got real attention. The analysis found the vital few and cut the scorecard from 70 measures to 7, each tied to strategy. Roughly 20% of provider compensation now rides on that focused set, so those seven get owned and re-checked, not admired.
"Having that refined list of only the most important measures, and ensuring they link to your organization's strategy, was a big lesson learned for us." — Darren Eversole, Director of Finance, Carilion Clinic
Southern Ohio Medical Center: from 40 hours to 20 minutes
Southern Ohio Medical Center is a 211-bed nonprofit hospital serving rural southern Ohio. Its gap was operational and invisible. One person spent 40 hours a month, a full work week, hand-assembling data into the places it needed to go. That's a week of improvement time lost to copy-paste every month. After centralizing reporting, the same job takes 15 to 20 minutes, and the measures get re-checked often enough to matter.
"It took one person 40 hours a month to populate all that data in all the places it needed to go, and we've cut that down to 15–20 minutes." — David Richard, Director of Performance Improvement, Southern Ohio Medical Center
Albany Medical Center: a workforce gap analysis
When New York State launched its Medicaid redesign (DSRIP), Albany Medical Center Hospital led a provider network across five counties and faced a coming shift in workforce demand. Its gap analysis compared the current workforce against the one the new model would need, and projected a substantial rise in demand for primary care providers across its five-county network, along with gaps in primary-care practice accreditation. Those findings became a workforce transition roadmap: what to redeploy, retrain, and hire. (Source: New York State Department of Health, DSRIP mid-point assessment.)
Gap analysis as part of healthcare performance management
A gap analysis is a snapshot. Performance management is the movie: the loop that keeps gaps surfacing early and closing fast. ClearPoint is built for that loop, around the two things the data says matter. Every gap gets an owner, and every gap gets a next-review date.
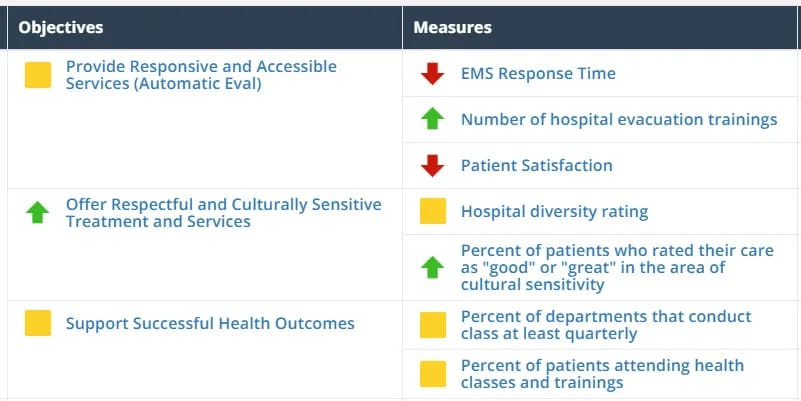
- See current performance at a glance. Track any measure, from patient safety to throughput to provider reviews, with red-amber-green status and trend, so a gap and its history are obvious in seconds.
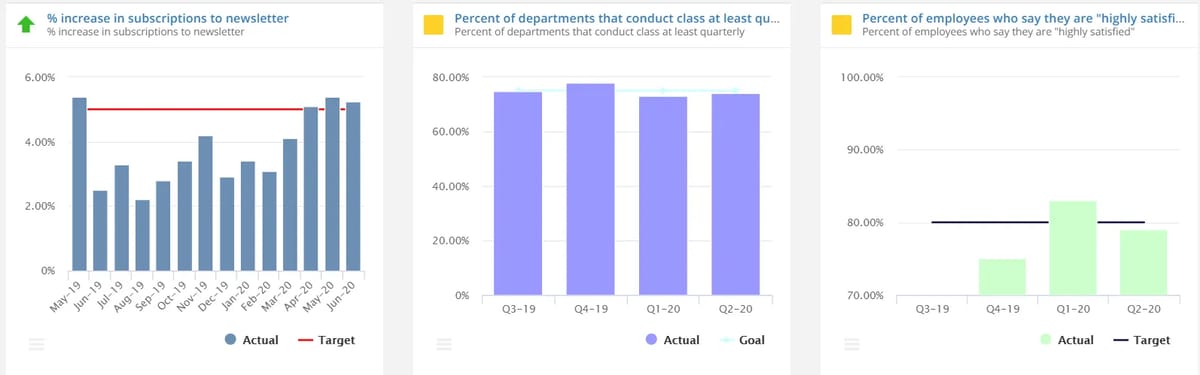
- Link every fix to the goal it serves. Connect improvement projects to the measures they're meant to move, so you can see whether the plan is closing the gap and report it cleanly to leadership and the board.
- Give every gap an owner and a due date. Assign it, name who's accountable, and collect updates in one thread. The analysis ends in a closed gap, not a file nobody reopens.
See how ClearPoint tracks your health system's strategy — book a demo
Close the gap, then keep it closed
A gap analysis is a promise your organization makes to its patients: the distance between the care you give and the care you should give will get smaller, on purpose. The framework is the easy half. The hard half is the name and the date that make a gap close. Book a free demo and see how ClearPoint keeps every gap owned, watched, and closing.
Common questions
When should you perform a gap analysis in healthcare?
When a measure that matters drifts red, when a new regulation or accreditation standard lands, before launching a program, and during annual planning. But timing is the smaller question. The one that decides the outcome is who will own the gap once you find it — settle that first, or the calendar won’t save you.
Which benchmark should a healthcare target be set against?
Use the standard that carries consequences for that measure: a regulatory threshold, an accreditation bar from PHAB or The Joint Commission, or a national benchmark such as the NDNQI falls median. Fall back on a board ambition only when no external standard exists, and record the source beside the target so later reviews test the same bar.
Who should own a gap that crosses departments, such as readmissions?
Name one person, not a team or a committee. Choose the leader who can convene the departments involved and move budget, then give each contributing department its own measure and owner underneath. That single name matters more than the method you use: measures with a named owner recovered twice as often as measures without one.
How often should a red measure be re-checked?
Set a specific date, usually monthly, and name who will look before the meeting ends. A standing check-in is the strongest lever in the data: measures their teams kept re-checking recovered about thirteen times as often as the ones left alone after a look or two. A vague “quarterly, probably” is how gaps go cold.