Nine strategic planning models compared for hospitals and health systems: when each works, where it breaks, a full hospital example and a free selection grid.
- No single model is sufficient on its own; the value comes from combining an environmental scan with an execution framework and reviewing both as conditions shift.
- For most hospitals and health systems, the strongest default is SWOT and PEST fed by the community health needs assessment, a Balanced Scorecard with a strategy map, and department OKRs reviewed monthly.
- Nine established models each answer a different healthcare question: SWOT and PEST read your internal and external environment, Porter's Five Forces maps competitive pressure, Scenario Planning prepares for uncertainty, the Ansoff Matrix frames growth, and the Balanced Scorecard, OKRs and Hoshin Kanri turn that reading into measurable action. Baldrige assesses the whole management system.
- The Balanced Scorecard fits healthcare because it tracks four perspectives at once-financial, patient care, internal processes, and learning and growth-so daily operations stay tied to long-term goals.
- Plan size and ownership travel with execution more than the model does: initiatives with a named owner are completed 2.5× as often (21.5% vs 8.7%), in ClearPoint anonymized platform data from plans run on the platform 2017–2024.
- Free, no form: a model-selection grid (Excel, opens in Google Sheets) with the complete hospital Balanced Scorecard from this article.
Strategic planning models help organizations in the healthcare sector work through hard problems. Patient needs change, regulations change, and technology moves fast. That makes strategic planning models a must.
These models speed up decisions and keep every action tied to the larger goals of better patient outcomes and operational performance. Below are the most effective strategic planning models used in healthcare, with our view on how each turns complex problems into clear, actionable strategies.
Here is the short answer. No single strategic planning model works on its own in healthcare. The hospitals that execute pair an environmental scan (SWOT, PEST, Porter’s Five Forces or scenario planning) with an execution framework (the Balanced Scorecard, OKRs or Hoshin Kanri). For most hospitals and health systems, the strongest default is SWOT and PEST fed by your community health needs assessment, a Balanced Scorecard with a strategy map, and department OKRs reviewed every month.
Below, you’ll find nine models compared by type of healthcare organization, a two-sentence definition of each, a complete Balanced Scorecard for a community hospital, and a free selection grid you can download without a form.
Which strategic planning models work best for a hospital?
The best model for a hospital is the one that answers its next question. Most hospitals need four answers, in this order: where do we stand, what could change, what will we commit to, and how will we know it’s working. One model rarely answers all four. So we stack them.
- Read the environment with SWOT and PEST. Feed both with your community health needs assessment, your quality data and your payer mix.
- Stress-test the big choices with scenario planning: a reimbursement cut, a nursing shortage, a competitor’s new ambulatory site.
- Commit and measure with a Balanced Scorecard and its strategy map. Keep it to ten objectives or fewer, each with one owner.
- Cascade and execute with OKRs or Hoshin Kanri in departments, reviewed monthly, with a quarterly strategy review for the board.
Growth decisions add the Ansoff Matrix. Hospitals that want to audit their whole management system, not just the plan, use the Baldrige Excellence Framework for health care.
The 9 models compared: which one for which healthcare organization
Use this table to build a shortlist. Each row says who the model suits, when to reach for it, and where it breaks.
| Model | Best fit (type of healthcare organization) | Use it when | Limits |
|---|---|---|---|
| SWOT and TOWS | Every hospital and health system; the usual first step for a community hospital | You open a planning cycle and need one shared read of strengths, gaps and pressures | A list, not a decision. Without TOWS or scoring, it rarely changes priorities. |
| Balanced Scorecard and strategy map | Hospitals and health systems of every size; the default execution frame | You must turn the plan into objectives, measures, owners and a review rhythm | Becomes a metric dump past ten objectives, and a report rather than a system without owners. |
| PEST and PESTLE | Systems exposed to policy and payer change; public health departments | Medicaid, reimbursement, labor or technology shifts will shape the next three years | Names the forces, not your response. Goes stale within a year. |
| Porter’s Five Forces | Systems in competitive metro markets; specialty and ambulatory groups | New entrants, payer leverage or consolidation threaten your market share | Built for priced, competitive markets. Weak for safety-net and public providers. |
| Scenario planning | Large systems and academic medical centers making capital or capacity bets | A major investment rests on assumptions you don’t control | Stays theoretical without trigger points and pre-agreed responses. |
| OKRs | Departments, service lines, digital and transformation teams | You need 90-day focus on a few measurable results inside a longer plan | Weak as the enterprise plan itself. Quarterly cycles clash with an annual budget. |
| Ansoff Matrix | Systems weighing new service lines, sites, markets or acquisitions | The plan has a growth question: more volume, new markets or new services | Says nothing about quality, workforce or margin. |
| Hoshin Kanri | Systems that run Lean or a daily management system; multi-hospital alignment | You need a few breakthrough goals cascaded to frontline teams | Demands leadership time. Stalls without monthly reviews. |
| Baldrige Excellence Framework (Health Care) | Hospitals pursuing performance excellence or a state or national quality award | You want to assess your whole management system against a national standard | Heavy. It assesses how you plan more than it tells you what to do. |
By type of organization: the stack to start with
| Organization | Start with | Execute with | Watch out for |
|---|---|---|---|
| Large or multi-hospital health system | PEST, scenario planning, Porter’s Five Forces | A system Balanced Scorecard, Hoshin Kanri or OKRs for system priorities | Objectives multiplying as every hospital adds its own |
| Nonprofit community hospital | SWOT and TOWS, fed by the community health needs assessment | A Balanced Scorecard with patients and community at the top | Running the CHNA implementation strategy as a separate plan |
| Rural or critical access hospital | SWOT and a short list of issues | A one-page scorecard with five to eight objectives | Copying a large system’s 40-measure scorecard |
| Academic medical center | Scenario planning and stakeholder planning across care, research and education | One Balanced Scorecard per mission, linked at the top | Three missions turning into three plans |
| Public health department | Community health assessment and PEST | A strategic plan linked to the community health improvement plan | Accreditation evidence living in a separate binder |
| Community health center (FQHC) | SWOT and the needs assessment | A Balanced Scorecard that includes funder and UDS measures | Reporting to funders replacing managing the plan |
Not in healthcare? The same comparison for cities, universities and nonprofits is in our guide to 20 strategic planning models and frameworks.
Before you pick a model: what the platform data says
We analyzed over 20,000 strategic plans run on ClearPoint between 2017 and 2024. That data can’t tell you which model is best. It can tell you which habits travel with the plans that get done. Two stand out, whatever the model.
Ownership. Across 52,247 objectives in 318 organizations, 77% have no named owner. Initiatives with a named owner are completed 2.5× as often (21.5% vs 8.7%).
Size and depth. Plans with 21 or more objectives complete 9.1% of their initiatives, against 11.8% for plans with 1 to 10. Plans with 4 to 8 measures per objective complete 15.1% of their initiatives, against 10.1% for plans with 3 or fewer.
So whichever model you choose, keep it to ten objectives or fewer, put one name on each, and give each four to eight measures. These are correlations, not guarantees. But they are the cheapest insurance a plan can buy.
Source: ClearPoint anonymized platform data, plans run on the platform 2017–2024. Objectives: 52,247 in 318 organizations. Initiatives: 90,305 in 315 organizations. Plan structure: 4,184 plans with at least one objective and one initiative. We see the structure of plans, never their content. How we read the data ›
Model 1: SWOT Analysis
In two sentences: A SWOT analysis lists an organization’s internal strengths and weaknesses next to the external opportunities and threats it faces. TOWS, its follow-up step, pairs each internal factor with an external one to turn the list into strategic options.

The SWOT Analysis is a basic strategic planning model for assessing both internal and external environments. It helps healthcare organizations pinpoint their Strengths, Weaknesses, Opportunities, and Threats, which lays the groundwork for informed decisions.
Knowing their strengths lets healthcare providers build on their core competencies, and naming weaknesses points to targeted improvements. Opportunities, often from new technology or policy changes, can be used to improve patient care and services. Recognizing threats, such as competitive pressures or regulatory challenges, is key to reducing risk.
See how ClearPoint tracks your health system's strategy — book a demo
In a hospital: if you’re a tax-exempt hospital, you already hold a strong input. Section 501(r) requires a community health needs assessment at least once every three years, plus an implementation strategy. Put its priorities straight into the opportunities box, then run TOWS to pair them with your strengths. Our guide to SWOT analysis in healthcare has worked examples.
Limits: A SWOT is a list, not a decision. Score each item, or run TOWS, before it reaches the board.
Model 2: Balanced Scorecard
In two sentences: The Balanced Scorecard, created by Robert Kaplan and David Norton in 1992, translates strategy into objectives, measures, targets and initiatives across four perspectives: financial, customer, internal process, and learning and growth. A strategy map draws the cause-and-effect links between those objectives on a single page.
The Balanced Scorecard, a strategic planning model widely adopted in healthcare, measures performance from several perspectives and ties daily operations to long-term strategic goals.
It breaks healthcare delivery into four key areas: financial performance, patient care, internal processes, and learning and growth. By evaluating these areas, healthcare organizations can see how well they are meeting their strategic objectives and make sure every part of the operation supports their vision.
The Balanced Scorecard turns abstract strategies into concrete actions and metrics. Healthcare providers use it to measure progress, find areas for improvement, and check that their business strategy is moving them toward better patient outcomes and operational excellence.
In a hospital: nonprofit hospitals usually change one thing. They put patients and community at the top of the strategy map and finance underneath, as stewardship.
About ClearPoint. Founded in 2008 by Ted Jackson and Dylan Miyake, who worked with Robert Kaplan and David Norton — the creators of the Balanced Scorecard — and have worked in strategy execution since 1999.
Limits: Past ten objectives, it turns into a metric dump. And a scorecard without owners is a report, not a management system. See the complete hospital example below.
Model 3: PEST Analysis
In two sentences: PEST analysis scans the political, economic, sociocultural and technological forces outside an organization, and PESTLE adds legal and environmental ones. It tells a hospital what is changing around it before it decides what to change inside.
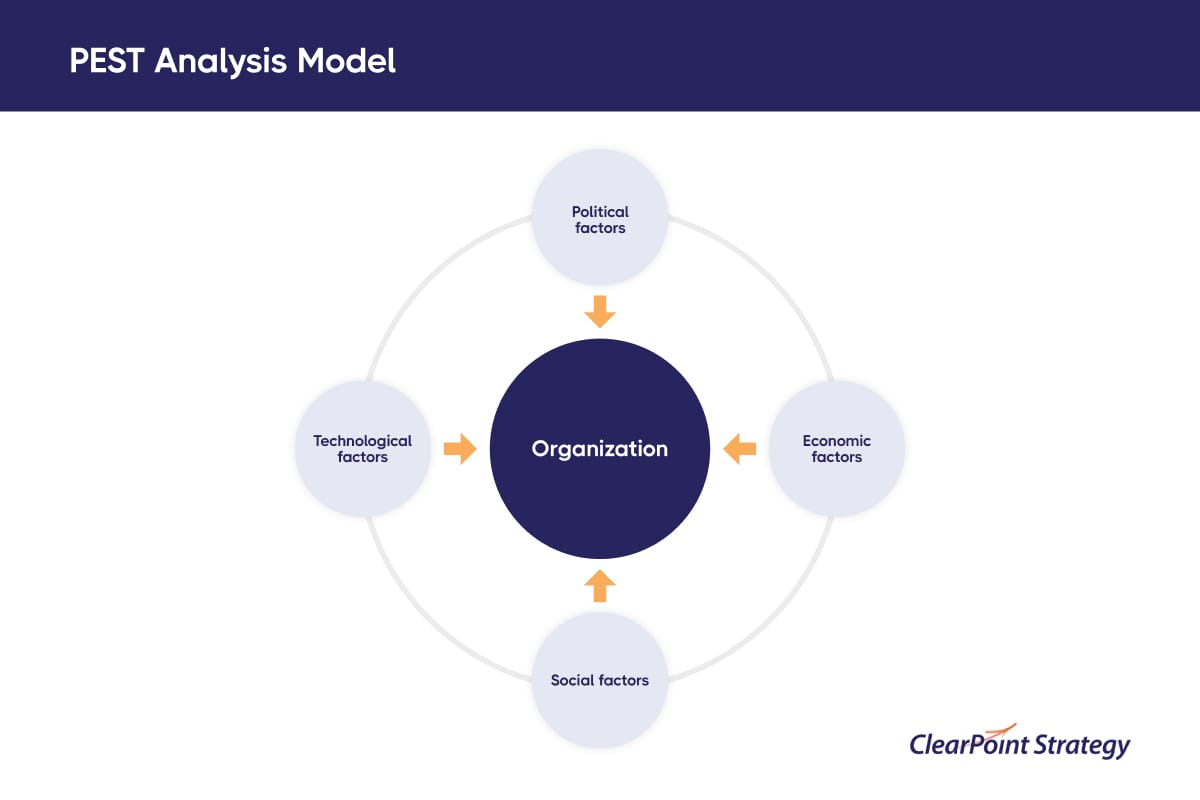
The PEST Analysis is a popular strategic planning model in healthcare that helps organizations get ahead of external factors that could influence their strategic direction.
It examines political, economic, sociocultural, and technological factors to give a full view of the external environment. In healthcare, PEST Analysis helps organizations anticipate changes in healthcare policy, economic shifts, social trends, and new technology.
In a hospital: Medicaid eligibility, Medicare payment rules, price transparency, the nurse labor market, an aging catchment area and AI in diagnostics all land in this grid. Health systems often run PEST once a year and feed its top three shifts into scenario planning.
Limits: PEST names forces, not responses. It also ages fast: refresh it with every budget cycle.
Model 4: Porter’s Five Forces
In two sentences: Porter’s Five Forces, published by Michael Porter in 1979, rates five pressures on an industry: rivalry, new entrants, substitutes, buyer power and supplier power. In healthcare, the buyers are mostly payers, and the substitutes include retail clinics, telehealth and ambulatory surgery centers.
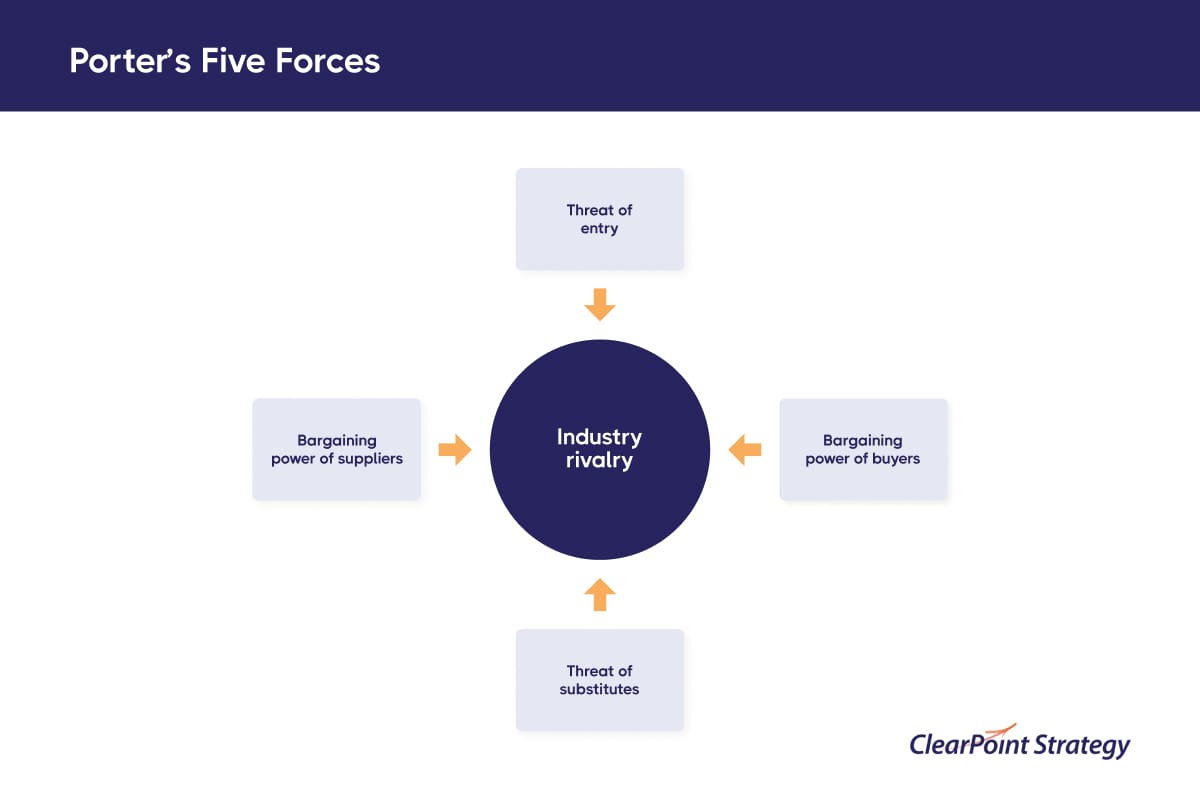
This strategic planning tool shows healthcare organizations how their industry works and where the competition stands. Created by Michael Porter in 1979, this model assesses five key forces: the threat of new entrants, the bargaining power of suppliers, the bargaining power of buyers, the threat of substitute products or services, and the intensity of competitive rivalry.
In healthcare, understanding these forces helps organizations make strategic decisions that handle competitive pressure. For instance, analyzing the threat of new entrants helps healthcare providers anticipate and prepare for new competitors. Similarly, understanding the bargaining power of suppliers and buyers can inform contract negotiations and patient care strategies. The threat of substitutes, especially emerging healthcare technologies, pushes organizations to keep innovating. The intensity of rivalry influences market positioning and service offerings.
With Porter’s Five Forces, healthcare organizations can build strategies that respond to current competition and shape their future position in the market.
In a hospital: the buyers are mostly payers, and the substitutes include retail clinics, telehealth and ambulatory surgery centers. The model answers one sharp question: who can take our best patients, and how?
Limits: The model assumes a priced, competitive market. For safety-net, public and critical access hospitals, community need often matters more than rivalry.
Model 5: Scenario Planning
In two sentences: Scenario planning builds two to four plausible futures and tests your strategy against each one. Its output is a set of trigger points and pre-agreed responses, not a forecast.
Scenario Planning is a strategic planning tool that helps healthcare organizations deal with an uncertain future. Teams write detailed stories about different future scenarios so they are ready for a range of possible developments. It works well in healthcare, where technology, policy, and patient needs change quickly.
By considering different futures, from technological breakthroughs to shifts in healthcare regulations, healthcare providers can develop flexible strategies.
In a hospital: typical scenarios cover a reimbursement cut, a severe nursing shortage, a demand surge or a cyberattack that takes systems offline. The useful part is the trigger: “if this indicator crosses this line, we switch to plan B.”
Limits: Without triggers and owners, scenarios stay a workshop exercise. Keep them few and tie each one to a measure on your scorecard.
Model 6: Objectives and Key Results
In two sentences: Objectives and Key Results pair a qualitative objective with three to five measurable key results, usually on a 90-day cycle. They focus a team on a few results without replacing the enterprise plan.
Objectives and Key Results (OKRs) are a strategic planning model for setting and tracking specific, measurable business goals. You define objectives and link them to quantifiable results, so every strategic goal is actionable and aligned with the organization's vision.
In healthcare, OKRs are particularly effective for driving improvements in patient care, operational efficiency, and innovation. ClearPoint Strategy makes OKRs easier to run in healthcare settings with a platform that simplifies setting, monitoring, and reporting on objectives and results. Healthcare organizations use our tools to track progress, adjust strategies as needed, and keep every team member working toward the same strategic goals. With OKRs in ClearPoint, and the customization options it offers, healthcare providers can execute their strategy better.
Check out our OKR dashboard and bring transparency to your entire organization
In a hospital: an emergency department might set the objective “make the wait feel short” with key results on door-to-provider time, patients who leave without being seen, and boarding hours. Tie every OKR to one scorecard objective, and the two frameworks work together instead of competing.
Limits: OKRs are a weak enterprise plan. Quarterly cycles also clash with a hospital’s annual budget, so anchor them to the scorecard.
Model 7: Ansoff Matrix
In two sentences: The Ansoff Matrix, introduced by Igor Ansoff in 1957, sorts growth options into four boxes: market penetration, market development, product development and diversification. Risk rises as you move from selling existing services in existing markets to new services in new markets.
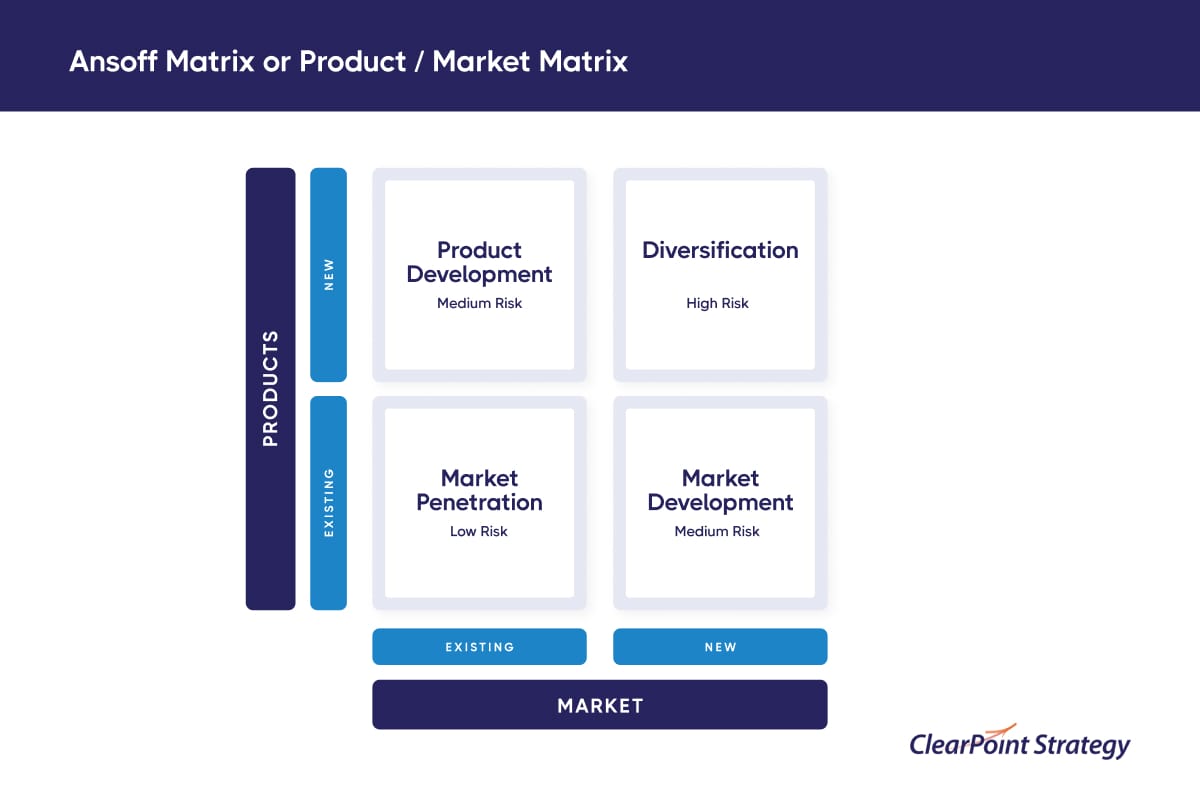
This model categorizes growth strategies into four quadrants: market penetration, market development, product development, and diversification. In the healthcare industry, the Ansoff Matrix is particularly useful for organizations looking to expand their market reach or diversify their services.
For instance, market penetration strategies might involve increasing patient numbers in existing services, while market development could focus on extending healthcare services to new geographical areas. Product development might include introducing new treatments or technologies, and diversification could involve adding entirely new services or patient care models.
Limits: Ansoff only answers the growth question. It says nothing about quality, workforce or margin, so it feeds the scorecard rather than replacing it.
Model 8: Hoshin Kanri
In two sentences: Hoshin Kanri, or policy deployment, picks a few breakthrough objectives and cascades them through every level using catchball, a back-and-forth negotiation of targets and means. Monthly reviews and an X-matrix tie each team’s work to the system’s priorities.
How hospitals use it: Health systems that already run Lean or a daily management system adopt Hoshin naturally. A system goal such as “zero preventable harm” becomes a unit-level target, a huddle-board measure and a monthly review. It is the most disciplined way to make frontline staff see the strategic plan in their own shift.
Limits: Hoshin asks for leadership time every month. Skip the reviews, and it collapses into a matrix nobody reads.
Model 9: Baldrige Excellence Framework (Health Care)
In two sentences: The Baldrige Excellence Framework is the U.S. national standard for performance excellence, and it has a version written for health care. It assesses seven categories, from leadership and strategy to customers, measurement, workforce, operations and results, to show how mature your management system is.
How hospitals use it: Hospitals use the framework’s self-assessment to find the weak link in how they plan, deploy and learn, often years before they apply for a state or national award. Its strategy category asks the questions a board should ask anyway: how do you develop strategy, deploy it, and know it is working?
Limits: Baldrige is heavy. It assesses how you plan more than it tells you what to plan, so pair it with a scorecard.
What about Lean and Six Sigma? They’re improvement methods, not planning models. They shine inside an initiative, such as emergency department flow or operating room turnover, once the plan has said which problems matter most.
Worked example: a Balanced Scorecard for a 250-bed community hospital
Here is one model applied end to end. The hospital is a composite: a 250-bed nonprofit community hospital with two urgent care sites. The numbers are illustrative. The structure is the one we see work.
Step 1: the inputs
- Community health needs assessment: behavioral health access and diabetes management top the list.
- SWOT: a strong orthopedic program and nursing reputation; emergency department boarding and rising nurse turnover; a growing retiree population; a competitor’s new ambulatory surgery center.
- PEST: payer mix moving toward Medicare Advantage, a tight nurse labor market, steady pressure to move procedures to outpatient settings.
Step 2: the strategy map on one page
Because the hospital is a nonprofit, patients and community sit at the top of the map. Finance sits underneath as stewardship: it funds the mission rather than defining it. Read the map from the bottom up. Nurses who stay make care safer and faster. Safer, faster care earns patients’ trust and the margin that pays for growth.
- Patients and community: better access to behavioral health; care patients would recommend.
- Quality and operations: no preventable harm; fewer avoidable readmissions; faster emergency care.
- Workforce and learning: keep and grow our nurses.
- Financial stewardship: a margin that funds the mission; growth in priority service lines.
Step 3: the scorecard
| Perspective | Objective | Owner | Lag measure: baseline → target | Lead measure | Initiative |
|---|---|---|---|---|---|
| Patients and community | Improve access to behavioral health | VP, Behavioral Health | Median days to first behavioral health visit: 24 → 10 | New behavioral health slots per week | Integrate behavioral health into four primary care clinics |
| Patients and community | Deliver care patients would recommend | Chief Nursing Officer | HCAHPS “definitely recommend” top-box: 68% → 74% | Discharge follow-up calls within 48 hours | Bedside shift report on every unit |
| Quality and operations | Eliminate preventable harm | Chief Medical Officer | CLABSI standardized infection ratio: 1.1 → 0.7 | Central-line bundle compliance | Daily line rounds in ICU and step-down |
| Quality and operations | Reduce avoidable readmissions | VP, Care Management | 30-day all-cause readmission rate: 15.2% → 13.5% | Discharges with medication reconciliation | Transitional care clinic for heart failure and COPD |
| Quality and operations | Get emergency patients seen faster | Chief Operating Officer | Median door-to-provider time: 38 → 20 minutes | Inpatient discharges before 11 a.m. | Provider in triage and a discharge lounge |
| Workforce and learning | Keep and grow our nurses | Chief Human Resources Officer | First-year RN turnover: 27% → 18% | New RNs enrolled in the residency | Twelve-month nurse residency program |
| Financial stewardship | Earn a margin that funds the mission | Chief Financial Officer | Operating margin: 0.8% → 2.5% | Days in accounts receivable | Revenue-cycle redesign |
| Financial stewardship | Grow priority service lines | VP, Strategy | Outpatient orthopedic and cardiology volume: +8% | Referral leakage to other systems | Physician liaison program and an orthopedic fast-track clinic |
Eight objectives, eight owners, one name per row. The table shows two headline measures per objective. The full scorecard in the free download carries four, a mix of lead and lag measures, with baselines and targets for each.
Step 4: the review rhythm
- Monthly: each owner updates their measures and writes a three-line status note. The operating council discusses the reds and yellows only.
- Quarterly: the executive team and the board quality committee review the strategy map, not the spreadsheet.
- Yearly: targets are reset with the budget. Every three years, the next community health needs assessment rebuilds the inputs.
Step 5: how the other models plug in
The scorecard doesn’t replace the other models. It gives them a home. SWOT and PEST produced the eight objectives. Scenario planning sets a trigger on the margin objective: if Medicare Advantage passes 45% of inpatient days, the revenue plan switches to its prepared scenario. OKRs run the emergency department objective 90 days at a time. Ansoff framed the service-line choice between orthopedics and a new market.
Download the model-selection grid (free, no form)
We turned this page into a workbook for your next planning retreat. No email, no form. It opens in Excel and Google Sheets.
- Tab 1, Selection grid: answer ten yes-or-no questions about your hospital. The grid scores the nine models and suggests the stack to start with.
- Tab 2, The 9 models: the two-sentence definition, best fit, when to use and limits of each model, ready to paste into a board memo.
- Tab 3, Hospital Balanced Scorecard: the complete example above, with four measures per objective, owners, baselines and targets.
Download the strategic planning model selection grid (.xlsx)
Take Your Healthcare Strategy to the Next Level with ClearPoint
While strategic planning frameworks and strategies may vary, the constant need for effective performance-tracking software remains. Traditional tools like Excel, despite their familiarity, fall short of providing clear, actionable insights for decision-making. They often lead to cumbersome, error-prone processes and lack real-time data analysis, hindering strategic decision-making and efficiency.
ClearPoint Strategy software improves this planning process. Our platform supports the most effective strategic planning models in healthcare and turns complex data into actionable insights. It works with every strategic planning model discussed here, whatever your strategic direction.
Get in touch with our team to see how ClearPoint Strategy can have a significant impact on your organization's strategic plans and overall performance.
See how hospitals and health systems use ClearPoint on our healthcare page, explore our strategic planning software, or read our guide to strategic planning in healthcare and our list of 25 healthcare KPIs. Ready to see your own plan in it? Book a 30-minute demo.
A hospital’s strategic plan is a promise to a community. The model is how you write it down. The monthly review is how you keep it.
We analyzed over 20,000 strategic plans run on ClearPoint between 2017 and 2024. 200+ organizations in government, healthcare, education and enterprise run their plans on ClearPoint. See how →
Common questions
Which strategic planning models work best for a hospital or healthcare organization?
No single model works alone. The hospitals that execute pair an environmental scan, such as SWOT, PEST, Porter’s Five Forces or scenario planning, with an execution framework such as the Balanced Scorecard, OKRs or Hoshin Kanri. For most hospitals, the strongest default is SWOT and PEST fed by the community health needs assessment, a Balanced Scorecard with a strategy map, and department OKRs reviewed monthly.
What is the best strategic planning model for a hospital?
If you can pick only one, pick the Balanced Scorecard with a strategy map. It turns a plan into objectives, measures, owners and a review rhythm, and it can hold the outputs of SWOT, PEST and scenario planning. Nonprofit hospitals usually put patients and community at the top of the map and finance underneath, as stewardship.
Can a hospital use the Balanced Scorecard and OKRs together?
Yes, and many do. The Balanced Scorecard holds the enterprise plan for three to five years, while OKRs run 90-day pushes inside departments or service lines, such as emergency department throughput. Link each OKR to one scorecard objective so the two never compete.
Which strategic planning model suits a small or rural hospital?
Start with a SWOT analysis and a short list of issues, then track five to eight objectives on a one-page Balanced Scorecard. Small hospitals rarely have a planning staff, so the model has to fit inside a monthly leadership meeting. Copying a large system’s 40-measure scorecard is the most common mistake.
How often should a hospital review its strategic plan?
Review measures monthly, the strategy quarterly, and targets every year with the budget. Rebuild the plan’s inputs when you rerun the community health needs assessment, which tax-exempt hospitals must complete at least once every three years.
What are strategic planning models?
Strategic planning models are structured frameworks used to guide organizations in developing, implementing, and evaluating their strategic plans. These models help organizations set goals, allocate resources, and define actions to achieve their objectives. Examples include SWOT Analysis, Balanced Scorecard, and PEST Analysis.
How can strategic planning improve the performance of an organization?
Strategic planning improves the performance of an organization by providing a clear roadmap for achieving goals. It aligns resources and efforts with strategic objectives, enhances decision-making, identifies potential risks, and enables organizations to adapt to changing environments. This leads to increased efficiency, effectiveness, and overall success.
How is strategic planning done?
Strategic planning is done through a systematic process that includes:
- Defining Vision and Mission: Establishing the organization's purpose and direction.
- Conducting Analysis: Performing SWOT or PEST analyses to understand internal and external factors.
- Setting Goals: Defining long-term and short-term objectives.
- Developing Strategies: Creating actionable plans to achieve the goals.
- Allocating Resources: Ensuring the necessary resources are available and properly allocated.
- Implementing Plans: Executing the strategies and plans.
- Monitoring and Evaluating: Continuously tracking progress and making adjustments as needed.
What is strategic planning in healthcare?
Strategic planning in healthcare involves developing long-term goals and strategies to improve healthcare delivery and outcomes. It includes assessing the current state, identifying future needs, and creating a plan to address those needs. This process helps healthcare organizations align resources, enhance patient care, and ensure sustainability.
Why is strategic planning important?
Strategic planning is important because it provides a structured approach for organizations to define their vision, set achievable goals, and create actionable plans. It helps organizations anticipate future challenges, allocate resources effectively, and stay focused on their long-term objectives. In healthcare, strategic planning ensures that resources are used efficiently to improve patient care and adapt to industry changes.